
Why maxillary and sphenoid fungal balls are markers of lost mucociliary clearance
A sinus fungal ball is one of the most visually persuasive findings in sinus surgery. The dense fungal material appears to be the disease, so removing it appears to be the treatment.
But the fungal ball is not the primary pathophysiological problem.
It is the visible consequence of a sinus cavity that has failed to clear its contents. Loss of mucociliary function produces mucostasis. Mucus and dead biological material remain within the sinus, and environmental fungi subsequently colonise this retained substrate.
The fungal ball is visible. The failed sinus is the disease.
This distinction changes both how fungal balls should be understood and what surgery should attempt to achieve.
The fungus colonises what the sinus has failed to clear
Fungi are ubiquitous. With sufficiently sensitive testing, fungal elements can be found in the nasal mucus of almost all healthy and diseased sinuses. In an immunocompetent person, these organisms are normally removed by the mechanical action of mucus and coordinated ciliary transport. A fungal ball can form only when fungal material remains within a sinus long enough to multiply and accumulate into a dense concretion.[1]
The process is comparable to leaving bread or orange peel on a kitchen bench. Fungus does not cause the food to remain on the bench. It colonises the biological material because that material has been left there.
The same sequence occurs within the sinus:
- Local mucociliary clearance fails.
- Mucus and biological debris accumulate.
- Environmental fungi colonise the retained material.
- Fungal accumulation provokes inflammation and a foreign-body response.
- Persistent inflammation produces epithelial injury and mucosal remodelling.
- Clearance deteriorates further, creating a self-perpetuating, nonfunctioning cavity.
The fungal ball is therefore not an isolated object that has entered an otherwise healthy sinus. It is a marker of mucostasis.

Sphenoid and Maxillary Sinus Fungal Balls
This also explains why the traditional concept of fungal ball as a consequence of ostial obstruction and poor ventilation is inadequate. Fungal balls can form despite a patent ostiomeatal complex, and common anatomical variants do not appear to be major determinants of their development.[1]
It is another example of why chronic sinusitis is not one disease. Fungal ball is not primarily a ventilatory disorder or an invasive fungal infection. It is secondary colonisation within a sinus that has lost effective mechanical clearance.
Its usually unilateral presentation also reflects the principle that true sinus disease is usually localised and anatomically consistent.
What causes the initial mucociliary failure?
The initiating event may differ between patients.
In some, the sinus may have a pre-existing local failure of mucociliary function. In others, dental disease, endodontic material, infection or another inflammatory event may temporarily disrupt clearance. Once mucus and biological material are retained, fungal colonisation and the resulting foreign-body reaction may convert a temporary disturbance into permanent mucosal dysfunction.
Age-related deterioration may also contribute. Fungal balls predominantly occur in older adults, and nasal mucociliary clearance becomes slower with increasing age.[2]
It remains uncertain whether mucociliary failure usually precedes fungal colonisation or whether an initiating event and longstanding fungal-associated inflammation progressively destroy the mucociliary apparatus. These pathways are not mutually exclusive. They converge on the same final process:
Failed clearance → mucostasis → fungal colonisation → inflammation and remodelling → further clearance failure.
Chronic inflammation can produce fibrosis, basement-membrane thickening, squamous metaplasia and other remodelling changes associated with loss of sinus function.[3]
The resulting cavity resembles bronchiectasis in the lower airway: retained secretions promote colonisation and inflammation, which further damage the clearance system. It is effectively bronchiectasis of the upper airway.
Different anatomy, but the same surgical endpoint
The maxillary and sphenoid sinuses do not fail for the same anatomical reason. They should not be treated as interchangeable cavities.
However, the philosophical intent of surgery is identical:
Eliminate the mucus sump and create a cavity in which irrigation, gravity and direct access can replace mucociliary clearance that has been permanently lost.
This is where the purpose of nasal irrigation is often misunderstood.
In a nonfunctioning sinus, irrigation is not principally a vehicle for delivering saline or medication. Its essential role is mechanical. The irrigation stream must enter with enough force to dislodge thick mucus, biological debris and crusting from dependent recesses. The mobilised material must then be able to leave the cavity.
The relevant question is therefore not simply:
Did irrigation enter the sinus?
It is:
Did irrigation enter with enough mechanical force to overcome mucostasis, and could the mobilised material escape?
A cadaveric study of maxillary sinus irrigation demonstrated this distinction. A standard antrostomy achieved complete sinus filling in 53% of specimens but produced major irrigation force in only 12%. After modified medial maxillectomy, complete filling occurred in 100% and major force in 94%.[4]
Penetration is not the same as effective lavage.
Maxillary sinus fungal ball: the inferior sump
The maxillary sinus is inherently dependent on mucociliary transport working against gravity.
Its natural ostium sits high on the medial wall, while the floor lies considerably below it. In some patients, the maxillary sinus extends below the floor of the nasal cavity and may pneumatise medially beneath it. Mucus must therefore be transported uphill over a substantial distance before it can leave through the natural ostium.
A middle meatal antrostomy enlarges this high opening, but it does not eliminate the dependent inferior reservoir.
This explains why apparently adequate surgery may remove the entire fungal ball yet leave the patient with persistent mucostasis, postnasal discharge, cacosmia, recurrent bacterial infection or continuing inflammation.
In our series of 28 patients undergoing wide middle meatal antrostomy for maxillary sinus fungal ball, mucostasis remained present in 39.3% at three months, 32.1% at six months and 17.9% at long-term follow-up.[5]

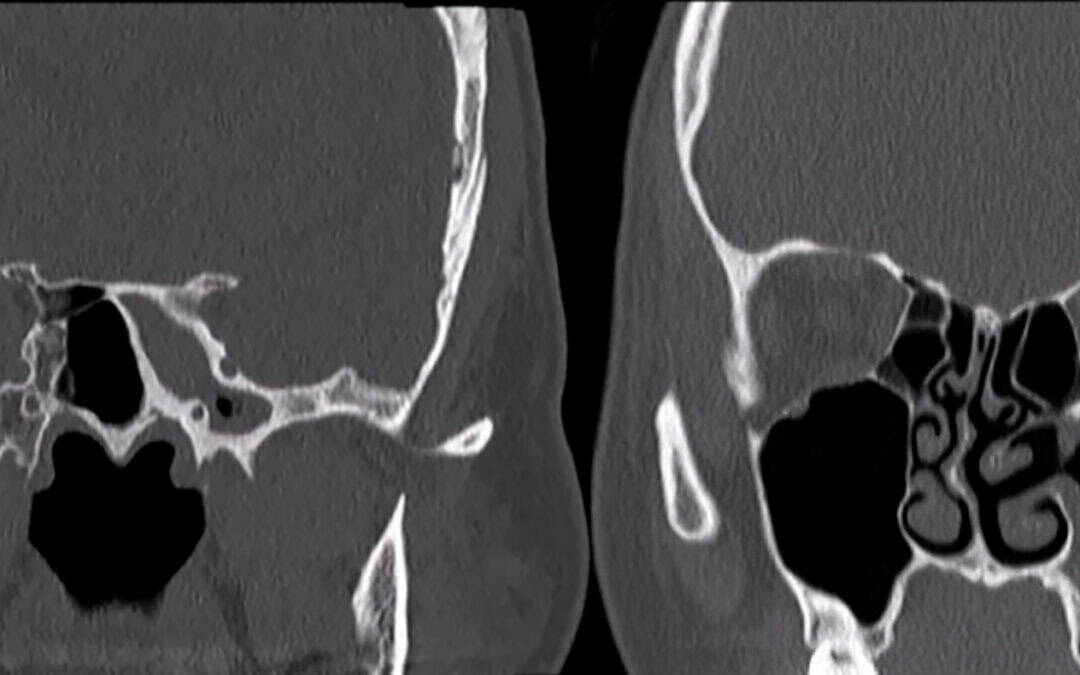
The classic hyperdense material is best seen on a soft tissue window
Patients with persistent mucostasis had significantly greater mucosal inflammation and used more postoperative antibiotics. Three required revision surgery, yet no recurrent fungal elements were found at revision.
The fungal ball had been successfully removed. The sinus had nevertheless remained diseased.
Reshaping the nonfunctioning maxillary sinus
When the maxillary mucosa cannot recover uphill clearance, surgery must compensate for that loss.
An endoscopic modified medial maxillectomy can:
- remove the medial wall towards the nasal floor;
- expose anterior and inferomedial extensions of the sinus;
- remove irreversibly diseased inferior mucosa;
- eliminate or obliterate the cavity extending below the nasal floor;
- allow irrigation to enter with sufficient mechanical force;
- permit passive, gravity-assisted clearance; and
- provide direct access for surveillance and postoperative cleaning.
The purpose is not simply to create a larger opening. It is to remove the inferior sump and allow nasal irrigation to mechanically replace the lost mucociliary system.
In a series of 57 patients with nonfunctioning maxillary sinuses treated using this approach, 91.2% had resolution of their presenting symptom and 91.2% had no persistent mucostasis. The cohort included several causes of maxillary dysfunction, including longstanding fungal ball.[6]
More surgery is not automatically better. The extent and design of surgery should be determined by whether the mucosa is likely to recover and whether a dependent, nonfunctioning space will remain. However, when the cavity has permanently lost clearance, repeatedly enlarging a high antrostomy does not correct the physiological problem.
Sphenoid sinus fungal ball: the retroclival sump
The sphenoid sinus presents a different anatomical problem.
Its ostium lies relatively high on the anterior sphenoid face. Behind and below this opening is the dependent retroclival recess, where mucus can pool. Intersinus and intrasinus partitions can create additional compartments that trap secretions and isolate parts of the sinus from mechanical lavage.
A limited sphenoidotomy may provide enough access to extract the fungal ball while leaving the retroclival sump and mucus-trapping partitions unchanged.
The operation has removed the contents but preserved the reason they accumulated.
Reshaping the dysfunctional sphenoid sinus
Because this dissection occurs close to the skull base, optic nerves and internal carotid arteries, a clear operative field is central to safe and complete endoscopic sinus surgery.
Functional sphenoid surgery may require:
- removal of the anterior sphenoid face down to the sinus floor and retroclival recess;
- removal of intersinus and intrasinus partitions;
- elimination of isolated mucus-trapping compartments;
- sufficient access for forceful mechanical lavage;
- an unobstructed pathway for irrigant and mobilised mucus to escape;
- direct postoperative endoscopic surveillance; and
- mucosal coverage of exposed bone where possible.
Experimental work supports this approach. Compared with a limited sphenoidotomy, sphenoid sinusectomy produced better irrigation distribution, greater force and improved clearance. Complete removal of the anterior face down towards the retroclival recess also reduced postoperative pooling of irrigant.[7]
Our sphenoid fungal-ball series provides an additional physiological clue. The fungal ball occurred in the smaller or non-dominant sphenoid sinus in approximately three-quarters of patients, while pneumatization patterns did not explain the side affected.[8]
The operative approach used the unaffected, usually larger sphenoid sinus to establish anatomical orientation. The rostrum, intersinus septum and mucus-trapping partitions were removed, and the affected cavity was reshaped to prevent retention in the retroclival recess. A vascularised mucosal flap was used to cover exposed bone.
All 23 operated cavities remained patent without mucostasis or persistent inflammation at last follow-up, with no recorded complications.[8]
The purpose of this operation is not radicality for its own sake. It is to leave a gravity-dependent sphenoid cavity in which irrigation can mechanically clear the surfaces that native mucociliary transport has failed to maintain.
Fungal recurrence is the wrong definition of success
Published fungal-ball surgery results often appear excellent. A systematic review reported an overall treatment success rate of 98.4%.[9]
However, most studies defined success as absence of recurrent fungal material or continuing sinus infection. Those endpoints do not establish that mucociliary function recovered or that the cavity remained free of mucus retention.
A 2026 series of 57 maxillary fungal balls illustrates the problem. No fungal recurrence was observed, yet 14% developed narrowing or closure of the antrostomy, 12% reported persistent postnasal discharge and 8.8% had mucus retention on the maxillary sinus floor.[10]
The fungal endpoint was excellent. The functional endpoint was not.
A meaningful definition of surgical success should include:
- absence of mucostasis;
- healthy or stable mucosa;
- resolution of symptoms;
- a patent and endoscopically accessible cavity;
- effective mechanical clearance with irrigation;
- freedom from recurrent bacterial colonisation;
- reduced antibiotic use; and
- no continuing need for repeated suction or debridement.
Future fungal-ball studies should report these functional outcomes rather than treating absence of recurrent fungus as the sole endpoint.
Antifungal medication does not restore sinus function
A conventional fungal ball is non-invasive and usually occurs in an immunocompetent patient. In the absence of tissue invasion, systemic or topical antifungal treatment has no established role.[1]
Antifungal medication cannot restore ciliary function, remove a dependent sump or mechanically evacuate retained biological material.
The essential postoperative treatment is directed at the cavity: high-volume irrigation capable of mechanical lavage, endoscopic removal of retained mucus or crusting, control of continuing inflammation, and surveillance until the sinus is demonstrably self-maintaining.
The practical message for sinus surgeons
When a maxillary or sphenoid fungal ball is encountered, the most important question is not:
How do I remove all the fungus?
It is:
Why was this sinus unable to clear the biological material on which the fungus grew, and how will it remain clear after surgery?
The central principles are:
- The fungal ball is secondary colonisation of retained biological material.
- Mucociliary failure and mucostasis are the underlying disease.
- The maxillary sinus fails through its high ostium and inferior dependent reservoir.
- The sphenoid sinus fails through its retroclival sump and mucus-trapping partitions.
- The anatomical operations are different, but their functional endpoint is the same.
- Nasal irrigation must mechanically replace lost mucociliary clearance, not merely enter the sinus.
- An open ostium does not prove that a sinus is functioning.
- Absence of recurrent fungus does not prove restoration of sinus health.
Removing the fungal ball treats the product of failure. Surgery is complete only when the surgeon has also addressed the dysfunctional cavity that produced it.
Treat the failed sinus—not just its contents.
References
- Fokkens WJ, Lund VJ, Hopkins C, et al. European Position Paper on Rhinosinusitis and Nasal Polyps 2020. Rhinology. 2020;58(Suppl S29):1–464. doi:10.4193/Rhin20.600
- Ho JC, Chan KN, Hu WH, et al. The effect of aging on nasal mucociliary clearance, beat frequency, and ultrastructure of respiratory cilia. Am J Respir Crit Care Med. 2001;163(4):983–988. doi:10.1164/ajrccm.163.4.9909121
- Do TQ, Barham HP, Earls P, et al. Clinical implications of mucosal remodeling from chronic rhinosinusitis. Int Forum Allergy Rhinol. 2016;6(8):835–840. doi:10.1002/alr.21754
- Wong E, Sansoni ER, Do TQ-P, et al. Cadaveric assessment of the efficacy of sinus irrigation after staged clearance of the medial maxillary wall. Am J Rhinol Allergy. 2020;34(2):290–296. doi:10.1177/1945892419895172
- Cavada MN, Wong E, Orgain CA, et al. Fungal ball of the maxillary sinus and the risk of persistent sinus dysfunction after simple antrostomy. Am J Otolaryngol. 2020;41(4):102541. doi:10.1016/j.amjoto.2020.102541
- Seresirikachorn K, Png LH, Kondo M, et al. Endoscopic-modified medial maxillectomy for the nonfunctioning maxillary sinus. Am J Rhinol Allergy. 2023;37(5):611–615. doi:10.1177/19458924231175848
- Grayson JW, Cavada M, Wong E, et al. Effects of sphenoid surgery on nasal irrigation delivery. Int Forum Allergy Rhinol. 2019;9(9):971–976. doi:10.1002/alr.22371
- Meerwein CM, Seresirikachorn K, Lindsay B, et al. Sphenoid sinus fungal ball and reestablishing sinus function. Laryngoscope. 2024;134(12):4888–4892. doi:10.1002/lary.31635
- Fadda GL, Allevi F, Rosso C, et al. Treatment of paranasal sinus fungus ball: a systematic review and meta-analysis. Ann Otol Rhinol Laryngol. 2021;130(12):1302–1310. doi:10.1177/00034894211002431
- Nomura K, Hemmi T, Ishigaki K, Sugawara M, Kakuta R. Postnasal drip and antrostomy narrowing after surgery for maxillary sinus fungus ball. Tohoku J Exp Med. Published online April 9, 2026. doi:10.1620/tjem.2026.J021
Frequently Asked Questions About Sinus Fungal Balls
What is a sinus fungal ball?
A sinus fungal ball is a dense, non-invasive accumulation of fungal material within a paranasal sinus. It forms after mucociliary clearance fails, allowing mucus and biological debris to remain long enough for environmental fungi to colonise it. The fungal ball is therefore a marker of a dysfunctional sinus cavity, not the primary disease.
Is a sinus fungal ball the same as invasive fungal sinusitis?
No. A conventional fungal ball is non-invasive and usually occurs in an immunocompetent person. Invasive fungal sinusitis involves fungal invasion into mucosa, blood vessels or surrounding tissue and is a different, potentially life-threatening condition requiring urgent treatment.
Why are fungal balls most common in the maxillary and sphenoid sinuses?
Both cavities contain dependent spaces that rely heavily on mucociliary transport working against gravity. The maxillary sinus has a high natural ostium above an inferior reservoir. The sphenoid sinus has a retroclival sump and may contain partitions that trap mucus.
Is removing the fungal ball enough?
Not always. Removing the fungal material can prevent fungal recurrence while leaving persistent mucostasis, inflammation or bacterial colonisation. Surgery should also address the nonfunctioning cavity so it can remain clear after the operation.
Are maxillary and sphenoid fungal balls treated with the same operation?
No. Their anatomical problems differ. Maxillary surgery may need to address an inferior reservoir below a high ostium, while sphenoid surgery may need to open the retroclival recess and remove mucus-trapping partitions. The shared endpoint is elimination of mucostasis and restoration of a maintainable sinus cavity.
Why is nasal irrigation important after fungal-ball surgery?
When native mucociliary transport cannot recover, irrigation becomes an external mechanical clearance system. It must reach the dependent recesses with enough force to mobilise retained mucus and debris, and the cavity must allow that material to escape.
Are antifungal medications needed for a sinus fungal ball?
Usually not. A conventional fungal ball is non-invasive, and antifungal medication does not restore mucociliary clearance or remove a dependent mucus sump. Treatment is primarily surgical, followed by irrigation, endoscopic care and surveillance appropriate to the cavity.